March 20, 2011

Infected (Mycotic) Aortic Aneurysm

An axial CT image shows a saccular aneurysm (arrowheads) arising from the infrarenal abdominal aorta (arrow), with periaortic soft tissue attenuation and fat stranding. Infected aortic aneurysm was confirmed at surgery.

Facts
  • It is a consequence of infectious aortitis with wall being weak and ruptured forming a false lumen or pseudoaneurysm
  • Most common location = infrarenal aorta
  • Most common causative agent = Salmonella
  • Route of infection = hematogenous, contiguous seeding, traumatic/iatrogenic inoculation
  • Mycotic = infection not confined only to fungus (use of mycotic aneurysm can be misleading)

Imaging
  • Aneurysm mostly saccular
  • Aneurysm size ranging from 1-10 cm
  • Around aneurysm: gas, soft tissue stranding, fluid
  • Can be confused with neoplasm, infected lymph nodes or hematoma

Reference:
Restrepo CS, Ocazionez D, Suri R, Vargas D. Aortitis: imaging spectrum of the infectious and inflammatory conditions of the aorta. RadioGraphics 2011;31:435-451.

March 15, 2011

Nuclear Accident And Potassium Iodide


Given the current situation in Japan, some of you may be interested in this topic.
The full FAQ is located at the National Regulatory Committee (NRC) website, here.

Potassium Iodide
  • Blocks thyroid uptake of radioactive iodine, therefore it reduces the risk of thyroid cancers that might be caused by exposure to radioactive iodine that could be dispersed in a severe nuclear accident
  • It is ingested, then taken up by thyroid gland -- if taken in a proper dosage at an appropriate time, it saturates the thyroid gland so that inhaled or ingested radioactive iodine will not be accumulated in the thyroid
  • Two KI tablets will protect the thyroid gland for approx 48 hours
  • Population within 10 mile emergency planning zone to the nuclear power plant are at the greatest risk of exposure to radiation, therefore KI is provided to protect them from effect of exposure after an accident
  • Best protective measures for nuclear accident are evacuation and sheltering. KI tablets are used to supplement evacuation or sheltering
Image from www.ask.com

March 10, 2011

Hyperdense Middle Cerebral Artery Sign

Axial CT image (narrow window) shows a hyperdense left MCA, representing an intraluminal thrombus.

Hyperdense MCA Sign
  • Visualization of high density middle cerebral artery due to presence of intraluminal thrombus
  • Specific sign for thrombotic MCA occlusion, but it is not sensitive
  • Associated with poor prognosis and higher risk of hemorrhage if thrombolyzed
  • Early resolution indicates successful reperfusion and favorable outcome after thrombolysis

Imaging Differentials
  • Intraluminal thrombus
  • High hematocrit (usually bilateral)
  • Calcified plaque (usually bilateral)

Reference:
Rabinstein AA, Resnick SJ. Practical Imaging in Stroke: a Case-based Approach, 2009.

March 6, 2011

False Positives in the National Lung Screening Trial (NLST)

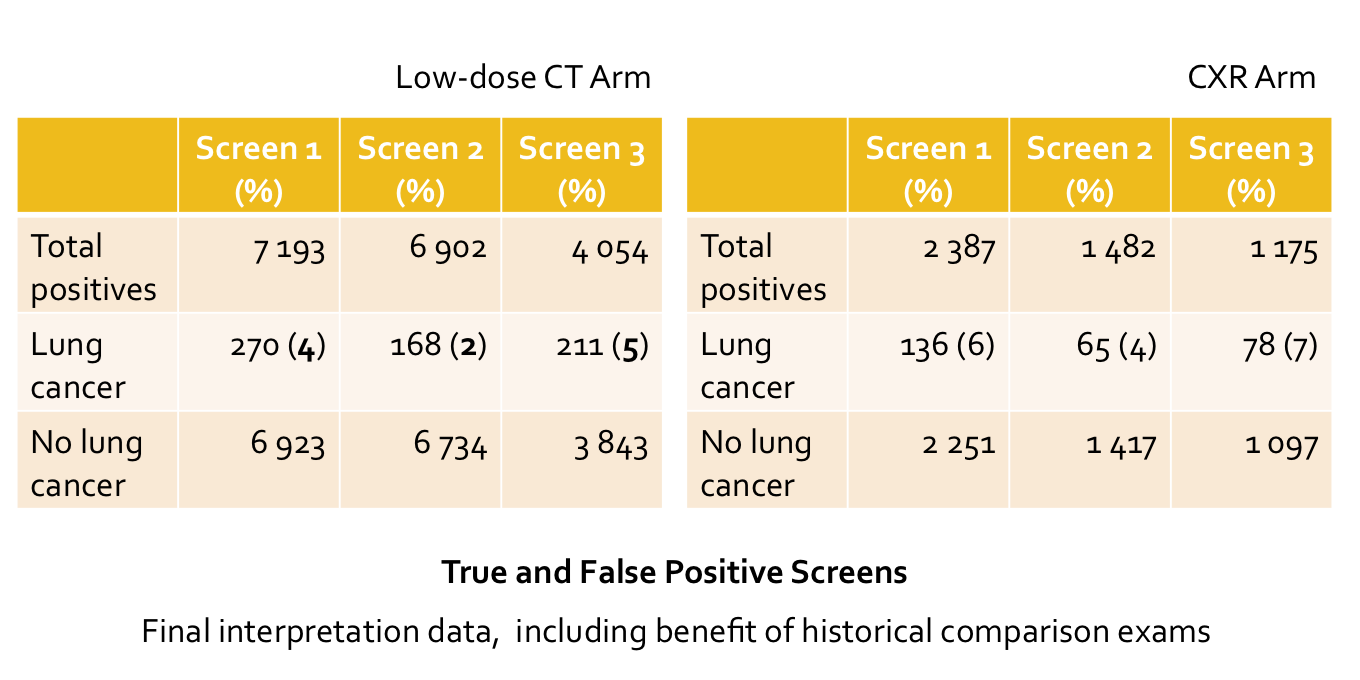
The tables show data from the NLST, with true and false positive screens at screening round #1, 2 and 3.

  • NLST is a randomized control trial studying the effect of low-dose CT screening vs. CXR in reduction of lung cancer-specific mortality. The interim result had been announced in October 2010, which showed a 20% reduction in mortality of those who had screened with low-dose CT.
  • Overall positivity rates (non-calcified nodule 4 mm or greater in size and other findings potentially related to lung cancer) for the NLST are 24.2% at low-dose CT, and 6.9% at CXR
  • Of all positives, only 2-5% (at CT) and 4-7% (at CXR) of cases are truly lung cancer.
  • Number of false positives are relatively high.
  • To reduce false positives, systematic and multidisciplinary approach in establishing the regimen for low-dose CT lung cancer screening is needed.
Reference:
Gierada DS. RSNA 2010

March 1, 2011

Lymphoepithelial Cysts in HIV

An axial CT image of the neck shows small cysts in bilateral parotid glands (stars). Cervical lymphadenopathy is present (not shown).

Facts: Lymphoepithelial Cysts in HIV
  • First described in 1988 in 18 males with painless facial swelling
  • Incidence: 3-10% of HIV-positive individuals
  • Can occur before HIV seroconversion
  • Can occur at any CD4 cell count
  • Unknown etiology
Imaging
  • Multiple, bilateral cysts of parotid glands
  • Cervical lymphadenopathy
  • Imaging differential diagnosis: bilateral Warthin's tumor, cystic pleomorphic adenoma, Sjogren's disease, branchial cleft cyst

Reference:
Lufkin RB, et al. Teaching Atlas of Head and Neck Imaging, 2000.

ShareThis